World & Politics7/10
Physician Argues Foreign Doctors Fill Gaps Created by U.S. Medical School Shortfall
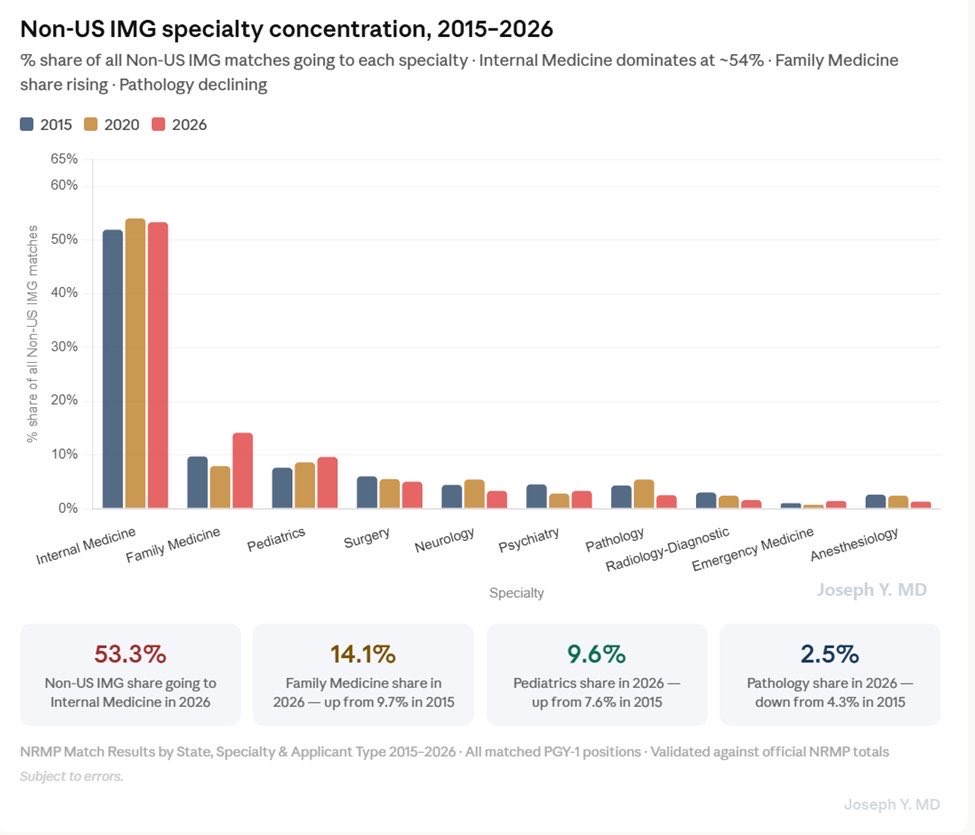
Dr. Joseph Younis responds to claims of H-1B fraud among residency programs, arguing that international medical graduates fill primary care and rural positions because U.S. medical schools produce far fewer graduates than available residency slots. He contends the root problem lies in medical school admissions, not in the programs or the IMGs themselves.

Original post · 2 min read
Again, the vast majority of this is not H1B fraud.
What you’re looking at is a cherry-picked list of community programs that are forced to accept IMGs because U.S. medical schools train 15,000 less medical graduates compared to available residency spots. In 2025, for example, there was 52,577 American college students who applied to medical school and only 22,262 were accepted. BUT, in 2025 there was also ~40,993 residency slots. When you add U.S. MDs and U.S. DOs applying to residency in 2025 you got roughly 27,498. That’s 13,495 short.
Who fills them? Two: U.S. IMGs (American international medical graduates) and non-U.S. IMGs (those are the “foreign” doctors you’re referring to).
Now, where do these IMGs match? Overwhelmingly in primary care and rural-suburban programs, which historically are areas US MDs don’t prefer. However, AND THIS IS IMPORTANT: JUST BECAUSE US MDs DONT PREFER IT DOES NOT MEAN THEY WOULDNT DO IT IF THAT WAS THEIR ONLY OPTION. Check charts below.
The evidence shows that 67-85% of US MDs would rather take ANY specialty and program over waiting just one more year to try again.
So what does this all mean?
1. The problem is not IMGs
2. The problem is not residency programs
3. The problem is upstream, at the medical school level. Why do we have ~52,000 Americans trying to get into med school and we turn away 58% of them?
4. IMGs are filling a need in a vacuum we created. Getting rid of IMGs would collapse healthcare in its current state
5. No, it’s not true that “Americans wouldn’t take those jobs anyway.” This is a scapegoat that lacks nuance. The match data is evidence against it. We shouldn’t invent arguments to mask bad policy
6. Bad policy persists only when incentives are involved. So who’s involved is the question you should be asking instead of racially targeting doctors.
7. The truth is we do need a diverse workforce, data shows patient-physician congruence is an important aspect of care management
8. We need to stop screwing over American students
It can all be true. This is a complex issue that’s cemented for 100 years now.
Expose H1B Fraud @JobsNowPaperLook at this chart.
These are American residency programs.
Red = foreign resident doctors.
Grey = Americans.
Some hospitals are almost 100% foreign. A lot of these doctors came in on visas. Some have been tied to fake credentials and USMLE cheating scandals.
I pay the premiums. I wait months to be seen. Taxpayer-funded Medicare GME money(over $21 billion a year) is training these foreign doctors instead of Americans.
And I DO NOT even trust these doctors !
Why should we keep funding this?
♥ 244 · ⟲ 39 · 👁 31.1KView on X ↗





